

EDITOR’S 1-MINUTE CLINICAL BRIEFING
Folic Acid vs. Methylfolate (5-MTHF) After 40: The MTHFR Paradigm
- The MTHFR Gene Reality: Between 40% and 60% of the population carries a genetic polymorphism in the Methylenetetrahydrofolate Reductase (MTHFR C677T or A1298C) gene. Individuals with homozygous C677T variants experience up to a 70% reduction in converting synthetic folic acid into its active biological form.
- The Hazard of Unmetabolized Folic Acid (UMFA): Ingesting high doses (>400–800 mcg) of synthetic folic acid saturates liver dihydrofolate reductase (DHFR) enzymes, causing synthetic unmetabolized folic acid (UMFA) to spill into systemic circulation—a condition linked to reduced Natural Killer (NK) cell cytotoxicity and the dangerous masking of Vitamin B12 deficiency.
- The Direct Bioactive Solution: Choosing L-Methylfolate (L-5-MTHF, Metafolin®, or Quatrefolic®, 400–1,000 mcg/day) bypasses the entire four-step enzymatic cascade, crossing the blood-brain barrier directly to reduce cardiotoxic homocysteine and synthesize dopamine, serotonin, and norepinephrine.
Understanding the true benefits and importance of folic acid requires examining one of the most critical paradigm shifts in nutritional biochemistry: the difference between synthetic folic acid and biologically active folate (L-5-MTHF). For decades, public health initiatives rightly celebrated folic acid for preventing neural tube defects in early pregnancy. However, for adults over age 40, relying on oxidized synthetic pteroylmonoglutamic acid (folic acid) inside cheap multivitamins carries significant metabolic limitations.
According to molecular genetics research published by the National Institutes of Health (NIH) and clinical cardiology trials indexed on PubMed, cellular methylation after 40 dictates cardiovascular plaque stability, cognitive sharpness, and DNA repair. Below is the definitive medical comparison of folic acid versus active L-methylfolate, the MTHFR gene protocol, and optimal dosing standards.
1. Head-to-Head Comparison Matrix: Folic Acid vs. Methylfolate (5-MTHF)
This detailed clinical matrix contrasts the biochemical properties, enzymatic requirements, and physiological impacts of synthetic folic acid versus bioavailable L-5-MTHF:
| Biochemical Characteristic | Synthetic Folic Acid (Pteroylmonoglutamic Acid) | Bioactive L-Methylfolate (L-5-MTHF / Quatrefolic®) |
|---|---|---|
| Chemical Form & Origin | Man-made oxidized synthetic compound used in food fortification | Naturally occurring, reduced, methylated form identical to cellular folate |
| Enzymatic Activation Required | Requires 4 distinct hepatic steps: DHFR (twice), MTHFD1, and MTHFR | Zero steps required; immediately bioavailable upon intestinal absorption |
| Impact of MTHFR Polymorphism | Severe bottleneck; 30% to 70% reduction in conversion efficiency | Completely bypasses MTHFR defects; works with 100% efficacy in all genotypes |
| Unmetabolized Folic Acid (UMFA) Risk | High risk; easily accumulates in blood when daily intake exceeds 400 mcg | Zero risk; utilizes natural feedback-regulated cellular methylation pathways |
| Blood-Brain Barrier Penetration | Extremely poor; cannot cross until converted to 5-MTHF | Superior; readily transported via folate receptor alpha into cerebral spinal fluid |
| Cardiovascular Homocysteine Reduction | Slow, inconsistent, highly variable among individuals | Rapid & potent; directly donates methyl groups to convert homocysteine to methionine |
| Standard Daily Clinical Dosage | 400 mcg DFE (Dietary Folate Equivalents) | 400 mcg – 1,000 mcg daily (up to 7.5–15 mg in clinical depression protocols) |
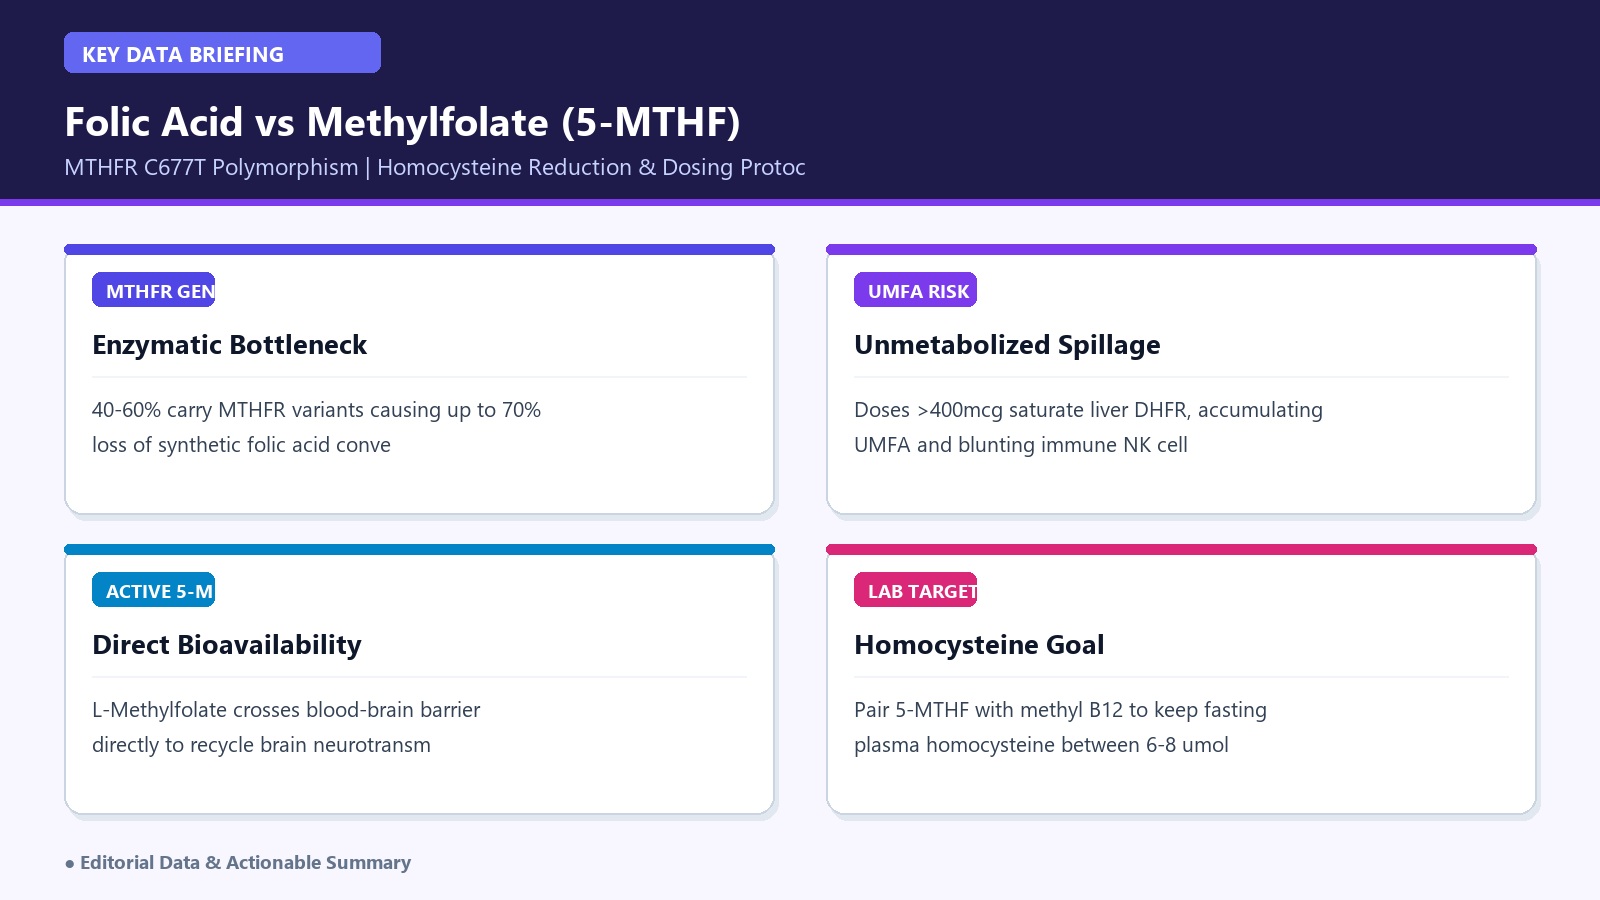
Figure 1: High-resolution clinical comparison of synthetic folic acid metabolism vs. bioactive L-5-MTHF.
2. The MTHFR Enzyme Bottleneck: Why 50% of Adults Struggle
Why is recognizing the true benefits and importance of folic acid so intertwined with genetic testing? In the human body, synthetic folic acid is biologically inert. Before your cells can utilize it to produce S-adenosylmethionine (SAMe) or synthesize purines for DNA repair, it must be reduced by the enzyme dihydrofolate reductase (DHFR) in the liver.
Human liver DHFR has extraordinarily slow activity—hundreds of times slower than in rodents. When dietary intake of fortified flour, enriched cereals, and high-dose synthetic supplements exceeds approximately 200–400 mcg per day, hepatic DHFR becomes completely saturated. As a consequence:
- Unmetabolized Folic Acid (UMFA) Enters the Blood: UMFA binds competitively to folate transport receptors, blocking the uptake of natural dietary folates. Epidemiological studies associate high circulating UMFA with dampened Natural Killer (NK) cell immune defense.
- The MTHFR Mutation Compound Bottleneck: If you carry the MTHFR C677T homozygous variant (roughly 10–14% of the population) or heterozygous variant (up to 45%), your enzyme’s thermal stability is reduced. You cannot efficiently convert intermediate folates into active 5-MTHF, resulting in stubborn hyperhomocysteinemia (elevated homocysteine >12 µmol/L).
- Neurotransmitter Synthesis Deficits: 5-MTHF is the mandatory methyl donor for regenerating tetrahydrobiopterin (BH4)—the rate-limiting cofactor for tyrosine hydroxylase and tryptophan hydroxylase. Without adequate 5-MTHF in the brain, the synthesis of dopamine, serotonin, and norepinephrine slows down, manifesting as midlife brain fog and low mood.
Clinical Evidence: Homocysteine & Cognitive Decline
In the Oxford VITACOG trial, elderly participants with elevated baseline homocysteine (>13 µmol/L) were randomized to high-dose B-vitamin therapy (including methylfolate and B12). The active treatment group experienced a 53% reduction in the rate of brain atrophy over two years compared to the placebo cohort, demonstrating that optimizing active methylation directly preserves brain parenchymal volume.

Figure 2: Morning routine pairing dietary folates from dark leafy greens with pure L-5-MTHF.
Benefits Protocol: 3. How to Choose & Dose: The 40+ Folate Protocol
To ensure you receive all the benefits of Vitamin B9 without the risks of unmetabolized synthetic compounds, apply these three clinical guidelines:
✅ The 3-Step Bioactive Folate Strategy
- Inspect the Supplement Label: Avoid products that list “Folic Acid.” Instead, look specifically for patented active forms: L-5-Methyltetrahydrofolate, Metafolin®, or Quatrefolic® (glucosamine salt of 5-MTHF, which offers the highest stability and water solubility).
- Always Pair with Bioactive Vitamin B12: Methylfolate donates its methyl group to cobalamin (B12) to convert homocysteine into methionine. If you take high-dose methylfolate while suffering from an undiagnosed B12 deficiency, you trigger the “methyl trap”—worsening neurological myelin damage. Always take 5-MTHF alongside 500–1,000 mcg sublingual methylcobalamin.
- Standard Maintenance Dosing: For general cardiovascular and neurological health after 40, a daily dosage of 400 mcg to 1,000 mcg (DFE) taken with morning breakfast is clinically optimal.
4. Clinical Traps: Masking B12 & Over-Methylation
When curating your regimen around the benefits and importance of folic acid, remain vigilant regarding these two clinical pitfalls:
- The Megaloblastic Anemia Masking Trap: Excessive synthetic folic acid (>1,000 mcg) corrects the macrocytic red blood cell size abnormalities caused by Vitamin B12 deficiency, making routine Complete Blood Count (CBC) tests look completely normal. Meanwhile, the underlying B12 deficiency silently continues to strip myelin from the spinal cord, leading to permanent neurological ataxia and paresthesia.
- Over-Methylation Symptoms in Sensitive Individuals: When individuals with slow catechol-O-methyltransferase (COMT) enzyme activity take large doses of methylfolate (e.g., >2,000 mcg), they may experience sudden irritability, racing thoughts, muscle tension, or insomnia. If this occurs, titrate down to 200–400 mcg daily or choose folinic acid (calcium folinate) instead.
5. Frequently Asked Questions (FAQ)
Can I get enough active folate from whole foods alone?
Dietary folates (from the Latin folium for foliage) are rich in dark leafy greens (spinach, romaine, kale), asparagus, broccoli, lentils, and avocados. However, natural polyglutamate folates are unstable, with cooking and heat destroying up to 50% of the nutrient. While a whole-food diet is essential, adults with MTHFR mutations or high homocysteine benefit significantly from targeted L-5-MTHF supplementation.
What is the target blood homocysteine level for optimal longevity?
While standard laboratory reference ranges consider anything below 15 µmol/L “normal,” preventative cardiology and functional medicine recommend keeping fasting plasma homocysteine between 6.0 and 8.0 µmol/L. Levels above 10–12 µmol/L double the risk of cardiovascular events, vascular dementia, and white matter brain hyperintensities.
Is Folinic Acid the same as Folic Acid?
No. Folinic acid (calcium folinate / leucovorin) is a reduced, non-methylated form of folate (5-formyltetrahydrofolate). It does not require DHFR for activation and is an ideal alternative for individuals who are sensitive to methyl donors (over-methylators) or experience anxiety when taking methylfolate.